



Referral Management Best Practices: A Weekly Quality Review
Review an operating referral process with a practical checklist. Look for missing owners, stalled handoffs and records that need attention, then assign a clear follow-up.

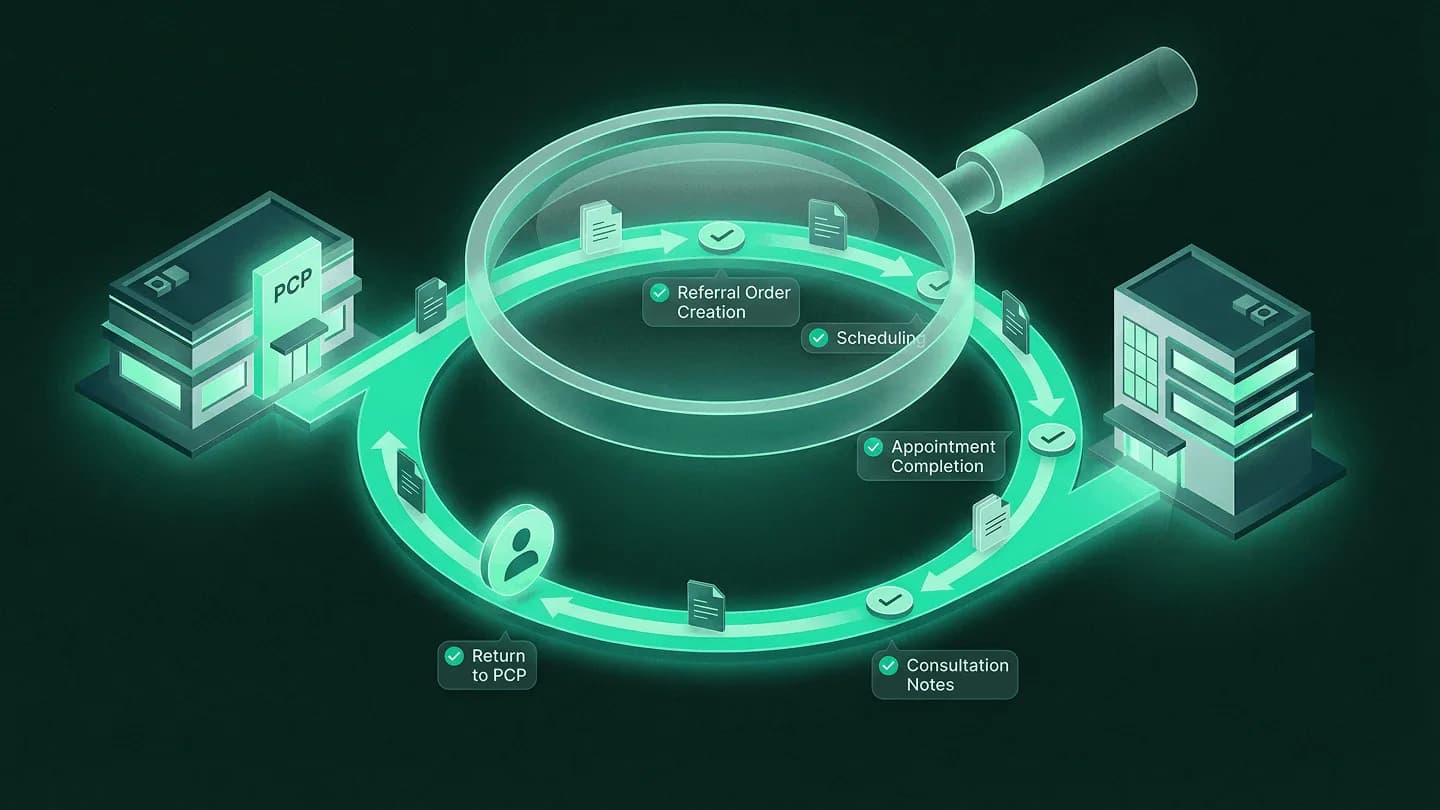
The useful question is more specific than whether the team is following up. Can another coordinator open a referral, understand its current state and identify who acts next without reconstructing the story from several inboxes?
AHRQ includes accountability, communication and follow-up among the activities involved in care coordination. The SAFER Guide on clinician communication also identifies referral tracking and clear responsibility for follow-up as parts of reliable information exchange. The review below turns those principles into a practical administrative exercise. Its weekly cadence is a starting option for your team to adapt, not a universal performance standard.
Start the review with an accountable sample
Begin with one queue, location or handoff your team can examine carefully. For example, review inbound referrals accepted during a specified period, or outbound referrals still awaiting an acknowledgment at the review cutoff. Write down that selection before opening individual records.
The selection matters when you interpret the findings. A review of known exceptions can identify useful problems, but it cannot tell you how often those problems occur across every referral. A convenience sample should not become an organization-wide failure rate in the next management report.
Record the queue, selection period, cutoff time and number examined. Keep the internal record references in the approved system, and bring only the information needed for the operating discussion. If you want to compare reviews over time, retain the same selection method or explain what changed.
Use the team's existing definitions for states such as received, accepted, awaiting information, scheduled and closed. When a label is unclear, flag the definition for the process owner instead of allowing each reviewer to invent a meaning. The referral metrics guide is the companion resource for deciding what the team's measures should count.
A useful review has a named leader and the people needed to resolve the chosen handoff. It does not need to become a meeting for every department. Invite a receiving-team representative when the question involves their acceptance of work, or the system owner when the recorded status does not match what staff can see.
Look for handoffs without an accepted owner
For each sampled referral, identify the last documented action, the next expected action and the person or team responsible for it. Then inspect the evidence supporting that assignment.
A message marked sent records a transmission. An assigned work item records a routing decision. Neither, on its own, answers whether the receiving team has accepted the work under your local process. Check the acknowledgment, queue entry or other record your organization uses for that purpose.
The IHI/NPSF referral guide emphasizes explicit expectations and accountability across referring clinicians, specialists and practice staff. Apply that principle to the handoff being reviewed, without assuming that one office controls the other office's workflow. IHI/NPSF referral guidance
Ask these questions in order:
- What action was requested, and where is it recorded?
- Which person or team is expected to act next?
- What shows that the handoff reached that person or team?
- What is the agreed follow-up or escalation path if it remains unresolved?
- Is the referring team able to see the current state?
Keep timing judgments tied to the applicable local workflow and qualified clinical direction. A weekly administrative review is not a replacement for handling time-sensitive work as it arrives. If the record raises a clinical question, use the organization's existing route to the appropriate clinical team.
Inspect records marked complete or closed
Include some records that appear finished. Otherwise, the review will only examine exceptions that the current workflow already knows how to display.
Start by asking what the status is intended to mean. An administrative task can be finished while the referral itself still has unresolved work. For example, a scheduling task marked complete may mean that an appointment was booked. It does not, by itself, document an attended visit or the receipt of a specialist report.
Check the relevant supporting record rather than treating the label as the evidence. Your process owner should define which documents, acknowledgments or recorded outcomes support each state. Keep separate fields or tasks where the organization needs to distinguish scheduling, visit status and returned documentation.
The SAFER Guide describes communication in both directions, including acknowledgment of a referral and return of findings to the referring provider. That is useful context for a record review, but the guide is not a substitute for your organization's decisions about task ownership and clinical follow-up. SAFER referral and consultation guidance, practice 1.2
Use a small review sheet like this one. It is an editorial template for local adaptation, not a validated clinical instrument.
| Review field | What to record |
|---|---|
| Internal record reference | A reference in the approved work system, with access limited appropriately |
| Observed issue | What the reviewer found, without guessing the cause |
| Supporting evidence | The status entry, acknowledgment or other record examined |
| Immediate correction owner | The person responsible for resolving this referral's administrative issue |
| Possible process cause | A hypothesis to investigate, distinct from the observed issue |
| Process action owner | The person responsible for any change to routing, instructions or system behavior |
| Revisit date | When the team will check the action and its effect |
The distinction between observation and explanation is useful. "The receiving queue has no acknowledgment" is an observation. "The receiving team ignored the referral" is an explanation that the available record may not support.
Separate recurring causes from isolated corrections
Fixing an individual record and improving a workflow are different assignments. Make both visible when they are needed.
Consider a hypothetical review in which a referral reached the intended office, but the shared queue still shows awaiting acceptance. The immediate task is to reconcile the status with the evidence. The process question is why that acknowledgment did not appear where staff expected it.
Possible explanations include a misunderstood status, an outdated destination, a routing rule or a manual step that the team did not know it owned. Treat these as questions to investigate. Do not turn the first plausible explanation into the recorded cause.
Group similar observations, then inspect a few examples with the people who do the work. Ask whether the same mechanism explains them. If it does, choose one bounded change that the process owner can evaluate. If the cases differ, retain the separate explanations rather than forcing them into a broad category such as "staff error."
Recurring categories can include missing acknowledgments, unclear ownership, information requested but not received, or inconsistent closure labels. They are useful organizing choices, not a national ranking of referral problems.
This review should identify where a deeper change is needed. Use the referral workflow implementation guide for designing and introducing that change. Keep detailed outreach sequences and contact policies with the patient outreach workflow, where their owners can maintain them.
Turn the review into assigned follow-up
End each issue with an action that a named person can complete. "Improve communication" is too broad to verify. "Confirm who acknowledges referrals in this receiving queue and update the handoff instructions" gives an owner something concrete to do.
For each action, record the owner, the change being considered, the evidence needed to close the task and a review date. If another team must accept the change, name that dependency rather than assigning responsibility to an entire department.
Separate immediate work from process work. A coordinator may resolve a record discrepancy while a supervisor checks the underlying instructions. A system owner may need to investigate a status mapping. Keep the referral's next action visible while that larger question is being addressed.
Choose a manageable set of changes. A long list of unassigned recommendations is less useful than a smaller set with clear accountability. Let the people doing the work confirm whether the action fits the actual workflow before calling it complete.
Check whether the previous fix held
Open the next review with the actions from the previous one. Confirm whether each was implemented, then examine appropriate later records for the same issue.
Use the same question and selection method where practical. If the workflow, queue or sample changed, document the difference before comparing results. "We did not find the issue in this sample" is a more accurate conclusion than "the problem has been eliminated."
Check for displaced work as well. If one queue looks clearer because unresolved items have moved elsewhere, include the receiving queue in the follow-up. Ask the team whether the change clarified ownership or created another manual check.
External benchmarks can provide context only when their populations, periods and definitions are relevant. Avoid adopting an unlabeled completion rate, scheduling target or outreach timetable as a universal standard. For this review, the most useful comparison is often whether your own defined process is being followed and whether a specific correction remains effective.
The review should leave the team with a clearer picture of its work: what happened, what remains open, who owns it and what will be checked next. To see how referral coordination automation keeps that picture current every day, book a demo.
Linear Health completely transformed how we operate. They replaced five disconnected tools we were using to manage referrals, scheduling, and patient outreach.
Frequently asked questions
What should a referral team review regularly?
How can we find handoffs without an owner?
What should we check before marking a referral closed?
How do we distinguish a one-off issue from a process problem?
Which referral benchmarks need caution?
Sources
- Agency for Healthcare Research and Quality: Care Coordination, accountability, communication and follow-up as care coordination activities.
- Office of the National Coordinator for Health Information Technology: SAFER Guide, Clinician Communication, practice 1.2, referral tracking, acknowledgment and responsibility for follow-up.
- Institute for Healthcare Improvement and National Patient Safety Foundation: Closing the Loop, A Guide to Safer Ambulatory Referrals in the EHR Era, expectations and accountability across the referral process.
